
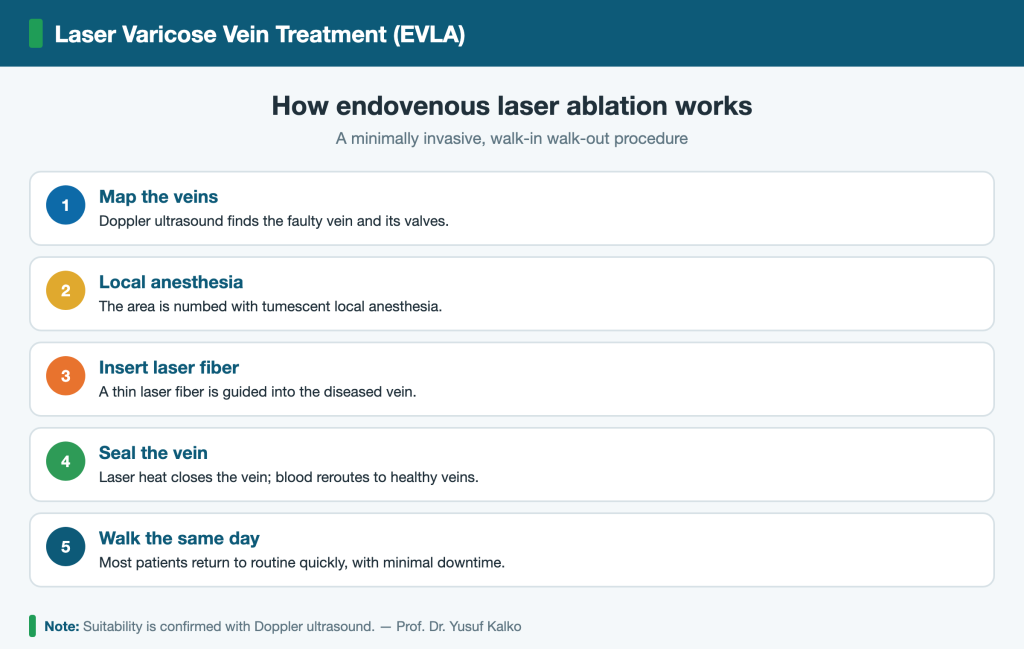
Endovenous laser ablation — EVLA, also written EVLT — closes a leaking vein from the inside using heat delivered through a thin fibre. There is no groin incision and no stripping: the vein is reached through a needle puncture, sealed along its length, and absorbed by the body over the following months. It is carried out under local anaesthesia and you walk out the same day.
In short: a fibre is passed inside the faulty vein under ultrasound, anaesthetic fluid is placed around it, and heat seals the wall as the fibre is withdrawn. Most people return to desk work within a day or two. The vein treated is one that a Doppler scan has shown to be refluxing — branches and spider veins are dealt with separately, by sclerotherapy or tiny punctures, often in the same sitting.
What EVLA is, and what it is not
The target is the trunk vein, not the bulges
The target of EVLA is a trunk vein — usually the great or small saphenous vein — whose valves no longer close. It is not a treatment for the visible bulges themselves: those are tributaries, and they are handled at the same appointment by other means. Understanding this prevents the most common disappointment, which is expecting the lumps to vanish because the main vein was lasered.
How the fibre seals the vein
The fibre delivers energy that heats the vein wall until collagen in it contracts and the vessel seals. Modern fibres emit the energy sideways in a ring rather than straight ahead, which spreads the heat evenly along the wall instead of concentrating it at one point; this is one reason post-procedure bruising and discomfort are lower than with older designs.
How it is performed
- Mapping. The leg is scanned standing so the refluxing vein, its branches and the point where it joins the deep system are identified and marked.
- Access. Local anaesthetic at one point, then a needle puncture into the vein — no incision — and a sheath is placed under ultrasound guidance.
- Positioning. The fibre is advanced and its tip is placed a safe distance below the junction with the deep vein. This distance is checked on the screen before any energy is given.
- Tumescent anaesthesia. Dilute anaesthetic fluid is injected around the vein along its whole length.
- Ablation. Energy is delivered as the fibre is slowly withdrawn, sealing the vein from top to bottom.
- Tributaries. Bulging branches are treated in the same sitting by foam or by phlebectomy through punctures that need no stitches.
- Compression and walking. Stockings go on before you stand, and you walk before leaving. Most people are home within the hour.
Why tumescent anaesthesia matters
The fluid placed around the vein is not simply painkiller. It does three jobs at once, and they are the reason thermal ablation is as safe as it is: it numbs the length being treated, it forms a heat sink between the hot fibre and the nearby nerves and skin, and it compresses the vein around the fibre so the wall is in close contact with the energy. Skipping or skimping on it is what produces nerve irritation and skin burns, which is why the several small injections along the leg are worth the few minutes they take.
If you would rather avoid those injections altogether, the heat-free alternatives — vein glue and mechanochemical closure — need only local anaesthetic at the entry point. Which is appropriate depends on the vein, not on preference alone; the comparison is set out in non-surgical varicose vein treatment.
Who is a candidate — and who is not
The typical candidate has reflux confirmed on ultrasound in a trunk vein, together with symptoms: aching and heaviness that worsen through the day, swelling at the ankle, night cramps, itching along a vein, or skin changes above the ankle. Treatment is also indicated after bleeding from a varicosity, after superficial phlebitis, or where a venous ulcer has formed or healed.
When another method is the better choice
Laser is not the right answer in every leg:
- Active deep vein thrombosis — the clot is managed first and treatment deferred.
- Significant peripheral artery disease — the arterial supply is assessed first, because the compression used afterwards may not be safe.
- Pregnancy — normally postponed; compression is used in the meantime and many veins improve after delivery.
- A vein running immediately beneath the skin — heat this close to the surface risks a burn or pigmentation, so glue, mechanochemical closure or phlebectomy is preferred.
- A very tortuous vein — a fibre cannot be passed reliably around tight bends.
- No demonstrable reflux on the scan — if the veins are not leaking, closing them will not relieve symptoms coming from elsewhere.
Recovery, week by week
| When | What is usual | What helps |
|---|---|---|
| The same day | Walking immediately; mild tightness along the vein | Compression on, short walks rather than bed rest |
| Days 1 – 3 | Bruising appears; aching along the treated line | Ordinary pain relief, daily walking, compression as advised |
| Week 1 | Desk work resumed for most; a firm cord may be felt where the vein was | Avoid heavy lifting, saunas and hot baths |
| Weeks 2 – 6 | Bruising fades; pulling when the leg is straightened eases | Return to fuller exercise as comfort allows |
| Months 2 – 6 | The closed vein is gradually absorbed; the cord softens and disappears | Follow-up scan where arranged |
What is normal afterwards — and what is not
- A firm, tender cord where the vein used to be: expected. It is the sealed vein, and it softens as it is absorbed.
- Bruising and tightness along the treated line: common after thermal treatment, settling over a few weeks.
- Pulling or tugging when straightening the knee in the early weeks, as the vein contracts.
- A numb patch of skin, if a small sensory nerve has been irritated; this usually recovers over weeks to months.
- Brown staining along the line of a treated tributary, which generally fades over months.
Heat-induced thrombus extension
One finding is specific to heat-based treatment and is the reason a follow-up scan is often arranged: heat-induced thrombus extension, where the clot that forms in the sealed vein reaches a little way into the deep vein at the junction. It is uncommon, usually causes no symptoms and most often settles on its own, but it is looked for deliberately rather than waited for, and it is occasionally treated with a short course of blood-thinning medicine.
Seek urgent medical care if you develop calf pain with swelling and warmth, sudden shortness of breath or chest pain after the procedure — these may indicate a clot in the deep veins or the lungs. Get prompt review for spreading redness with fever, a wound that discharges, a blistered or broken area of skin over the treated vein, or numbness that is worsening rather than settling. These are uncommon, but they are time-sensitive.
Laser compared with the other closed methods
| Method | How it closes the vein | Anaesthesia | Typically matched to |
|---|---|---|---|
| Laser (EVLA) | Heat from a fibre seals the wall | Local plus tumescent along the vein | Larger refluxing trunk veins |
| Radiofrequency (RFA) | Controlled heat in segments | Local plus tumescent along the vein | Similar indications; often less bruising reported |
| Vein glue (VenaSeal) | Medical adhesive bonds the walls | Local at the entry point only | Avoiding tumescent injections; rapid return to activity |
| Mechanochemical (MOCA) | Rotating wire plus sclerosant | Local at the entry point only | Veins close to skin or nerves, where heat is less desirable |
| Foam sclerotherapy | Foamed agent closes the vein | Usually none | Tributaries, residual and recurrent segments |
Laser compared with open surgery
| EVLA | Open surgery (stripping) | |
|---|---|---|
| Anaesthesia | Local with tumescent | Usually general or spinal |
| Access | Needle puncture | Incisions, including the groin |
| Hospital stay | Day case | Often overnight |
| Return to routine | Days | Typically one to several weeks |
| Scarring | Minimal | More pronounced |
| Where surgery still wins | – | Anatomy a catheter cannot negotiate |
Can the veins come back?
The sealed vein itself reopens only rarely. What people experience as recurrence usually has a different explanation: a tributary that was not treated at the time and enlarges later, reflux developing in a vein that was healthy at the first scan, or fine new vessels growing across the treated area. None of these means the ablation failed — they reflect the fact that the underlying tendency for valves to leak is not removed by closing one vein. A review scan picks up a developing tributary while it is still a small job, and a periodic vascular assessment is worth considering where there is a strong family history.
Why Choose Turkey (Istanbul)?
- Over 30 years of experience in cardiovascular and vascular surgery with Prof. Dr. Yusuf Kalko.
- Modern minimally invasive and hybrid techniques.
- English- and Arabic-speaking support for international patients.
- Easy access to Istanbul from the Gulf, Europe and beyond.
- Remote assessment before travel, then treatment and appointment planning.
How to Start From Abroad (Remote Consultation)
You can send your medical reports and scan images via WhatsApp for an initial assessment before traveling. We then plan your treatment and appointment in Istanbul, Turkey, and support international patients at every step.
To evaluate your veins with Doppler in Istanbul (Beylikdüzü) and plan suitable treatment, contact us on WhatsApp.
Related Pages
The heat-free alternative, and why it needs no tumescent injections: VenaSeal glue treatment.
Frequently Asked Questions
Is laser varicose vein treatment painful?
It is done under local anaesthesia and most people describe pressure and the small tumescent injections along the leg rather than pain. Aching and tightness along the treated vein for the first days is normal and ordinary pain relief is usually enough.
How long is the recovery?
Walking starts immediately and most people return to desk work within one to two days. Bruising and tightness settle over a few weeks, and the closed vein is absorbed over several months. Heavy lifting and intense training are usually paused briefly.
Can varicose veins come back after laser?
The treated vein rarely reopens, but new varicose veins can develop over the years because the underlying tendency remains. Untreated tributaries are the most frequent reason for an early recurrence, which is why a follow-up scan is useful.
Why is anaesthetic fluid injected all along my leg?
That is tumescent anaesthesia. It numbs the vein, separates it from nearby nerves and skin so the heat cannot reach them, and compresses the vein around the fibre so the energy works evenly. It is a safety step, not an optional extra.
Will the bulging veins disappear on their own?
Not reliably. Laser closes the trunk vein that feeds them; the bulges themselves are branches and are usually treated in the same sitting with foam or tiny phlebectomy punctures. Some shrink once the pressure is removed, but planning for them from the start gives a better result.
Do I need to wear compression stockings?
Yes, for a period set at the time, and it affects both comfort and the result. If you have reduced arterial circulation in the legs this is checked beforehand, because compression is not suitable for everyone.
When can I fly after the procedure?
Flying is usually deferred for a short period, then undertaken with compression stockings, good hydration and regular walking in the cabin. Confirm the interval before booking, since it depends on what was treated.
Do you treat international patients?
Yes. International and Gulf patients are seen in Istanbul with English- and Arabic-speaking support, and an initial remote assessment can be made from your reports and scan images before you travel.